

Measurement of renal function in patients starting on angiotensin-converting enzyme (ACE) inhibitors within one week after commencement of treatment or dose adjustment is compulsory, and failure to do so would be negligent.
Dietary change post-MI – the key aspect of lifestyle change
Recent research suggests that post-MI patients are not being optimally managed. Awareness and implementation of guideline recommendations could improve outcomes in this patient group.
It is astonishing with how little reading a doctor can practise medicine
“It is astonishing with how little reading a doctor can practise medicine, but it is not astonishing how badly he may do it.-(William Osler, Aequanimitas, Books and Men)
HOT TOPIC | Commissioning in the new NHS: what are the implications for cardiovascular and diabetes services?
The new coalition government of the United Kingdom (UK) has announced plans to change the NHS radically in England. The Department of Health has published two important documents Equity and excellence: liberating the NHS and Liberating the NHS: commissioning for patients. The implications for primary and secondary care, and for local authorities, mental health services and community providers, will be enormous. The changes are taking place at a rapid pace and every manager and clinician in the NHS will need to keep abreast of developments as they will affect the way in which we all deliver services in the future.
Screening for peripheral arterial disease: a real chance to improve patient care
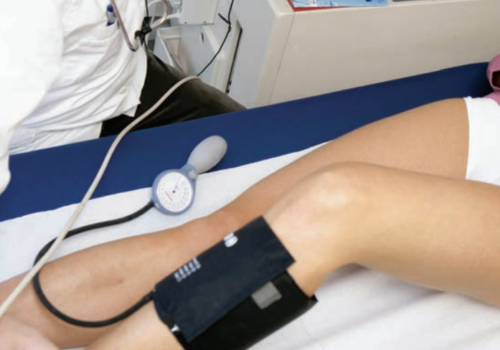
Symptomatic peripheral arterial disease (PAD) affects 3-5% of the population over 60 years of age. Many patients with PAD are unaware of their diagnosis, and hence may not have mentionedthe classical symptoms to their GP. The Edinburgh questionnaire is a validated tool thathelps identify susceptible patients. The questionnaire was administered to patients routinelyattending annual influenza immunisation clinics, in order to identify patients potentially at risk ofPAD. In all, 2.9% of the >65yr cohort were identified by the questionnaire as at risk of PAD.Opportunity was made for these patients to have their risk factors reviewed, and managementwas adjusted in line with the Target PAD algorithm. Reducing the risk factor profile of suchpatients improves quality of life scores, morbidity, and mortality. Periodic screening of an ‘atrisk’population may identify individuals who would gain considerable benefit from furtherevidence-based management.
What do the new QOF indicators mean for primary care?
The QOF quality and productivity (QP) indicators fall into three categories: prescribing, outpatient referrals and emergency admissions. What will these new indicators mean for primary care and how might they affect the prescribing of cardiovascular drugs and referrals to secondary care ?
The ‘no tears’ approach to medication reviews
Ten per cent of the annual NHS budget is spent on medication, with about 75% of this is prescribed in primary care. Ensuring that this money really improves patients’ health is vitally important. As the population ages, more people require increasing numbers of medications for chronic conditions and a third of elderly patients are taking four drugs or more for a spectrum of conditions. But this creates a major challenge – as research reveals that fewer than half of these patients take their medicines as prescribed. How can this challenge be addressed? This new series will provide simple practical guidance on how to conduct an effective medication review for a spectrum of long-term cardiovascular conditions.
Optimising risk factor modification and prevention of stroke
Prevention of stroke is a key component of the overall management of stroke. Primordial prevention strategies include avoidance of tobacco use, maintenance of an adequate level of physical exercise and optimal diet and weight, and avoidance of heavy alcohol intake. Several medical risk factors have been demonstrated clearly, and intervention to optimise these risk factors for primary prevention (of first stroke) and secondary prevention (of stroke in those known to have cerebrovascular disease) has a robust evidence base.
A local strategy to improve outcomes for TIA and stroke
We describe here a project that sets out to reduce the risk of stroke in patients suspected of having a transient ischaemic attack.
“Time is brain” – thrombolysis in acute stroke
“Time is brain” – thrombolysis in acute stroke – Mark Garside, Christopher PriceStroke is a common condition with long-term consequences. If symptoms are recognised early enough and patients are transported rapidly to hospital then there is the opportunity to administer treatments which may reduce long-term disability. We summarise the role of intravenous thrombolysis in the treatment of acute ischaemic stroke, including supporting evidence, how it is used in clinical practice, and possible future developments.
Thrombolysis for the treatment of acute ischaemic stroke
The new oral anticoagulants, and their use in stroke prevention
We have three new licensed anticoagulant agents–dabigatran, rivaroxaban and apixaban. Their use for stroke prevention in AF is discussed: primary care is central to their utilisation.


















